
The model emerged from his investigation of lymphatic anatomy, review of the available research, and clinical experience with kinesiology taping techniques. This work subsequently contributed to the development of professional education on lymphatic applications of kinesiology tape.
Kinesiology Taping for Lymphatic Uptake Augmentation
Understanding the proposed biomechanical mechanism, clinical application, and evolving scientific evidence
Christopher W. Harper, PT, DPT, OCS
Board-Certified Orthopedic Clinical Specialist
EduKT, Inc. | Active Lifestyles Physical Therapy
Introduction: Beyond Traditional Kinesiology Taping
Kinesiology tape has been used for decades in rehabilitation and sports medicine. Its applications include providing sensory feedback, modifying movement-related symptoms, and potentially assisting in the management of localized swelling.
One particularly intriguing application is its proposed ability to augment the lymphatic system’s natural uptake of interstitial fluid.
Between 2007 and 2009, I began investigating how a lightweight, elastic tape—applied without substantial compression—might influence lymphatic function. Existing explanations frequently emphasized lifting the skin to create additional space beneath the dermis or generating a negative-pressure effect. However, these explanations did not adequately account for the dynamic anatomy and physiology of initial lymphatic fluid uptake.
Through a review of the literature, discussions with anatomists, and clinical experimentation, I developed an alternative biomechanical model emphasizing skin deformation, tissue movement, and the mechanical behavior of initial lymphatic capillaries.
I originally presented this approach in educational settings and published a clinical explanation on this website in 2015. The model has subsequently been expanded through additional literature review and professional continuing education development, including material I authored for KT Tape’s clinical education program.
The purpose of this article is to explain that proposed mechanism, demonstrate the application principles, and distinguish the available scientific evidence from questions that remain unanswered.
Understanding the Lymphatic System
The lymphatic system is an essential component of fluid homeostasis and immune function.
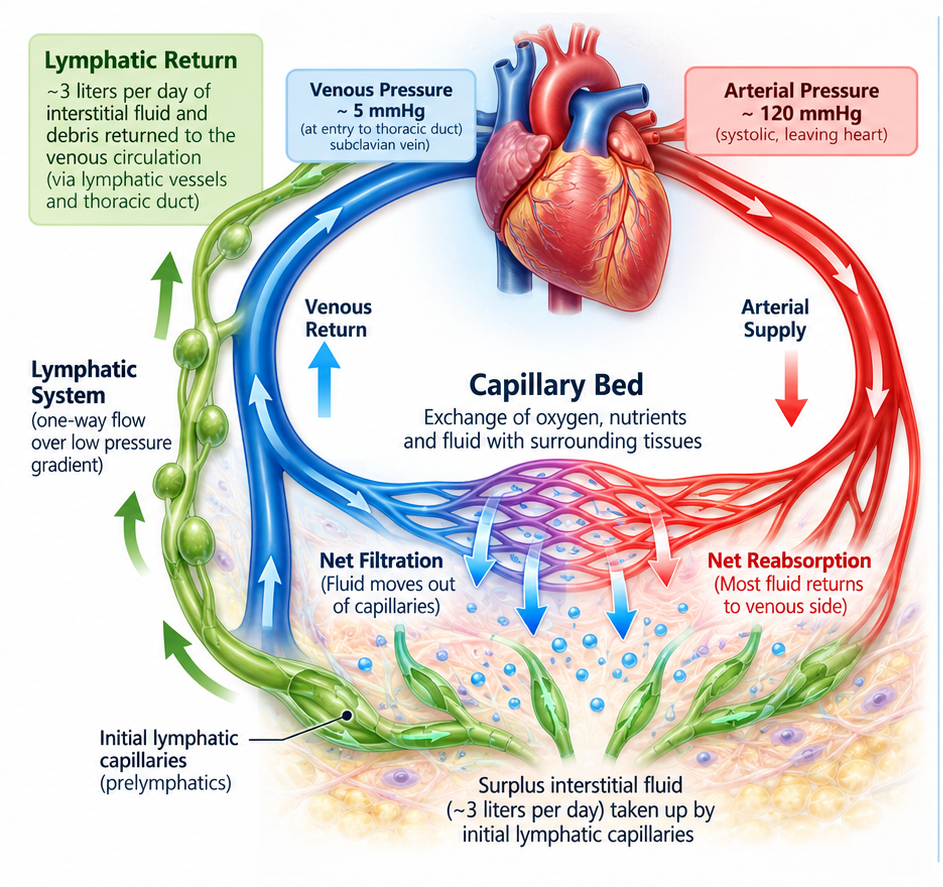
As blood circulates through the microvasculature, fluid and dissolved substances move between capillaries and the surrounding interstitial space. These exchanges are influenced by hydrostatic and oncotic forces, vascular permeability, and the characteristics of the surrounding tissues.
The lymphatic system collects interstitial fluid and transports it through progressively larger lymphatic vessels before returning it to the venous circulation.
Unlike the cardiovascular system, which has the heart as its central pump, lymph transport depends on several interacting mechanisms. These include intrinsic contractions of collecting lymphatic vessels, one-way valves, skeletal muscle activity, respiratory pressure changes, arterial pulsations, and deformation of surrounding tissues.
The initial lymphatic capillaries are especially relevant to the proposed mechanism of kinesiology taping.
How Fluid Enters Initial Lymphatic Capillaries
Initial lymphatic vessels have specialized endothelial junctions that permit interstitial fluid to enter when local mechanical and pressure conditions favor uptake.
Overlapping endothelial cell borders can function as primary, flap-like valves. These vessels are also mechanically connected to surrounding extracellular tissue through anchoring structures that help maintain vessel patency as tissue forces change.
This arrangement makes the interaction between tissue deformation and lymphatic uptake particularly interesting.
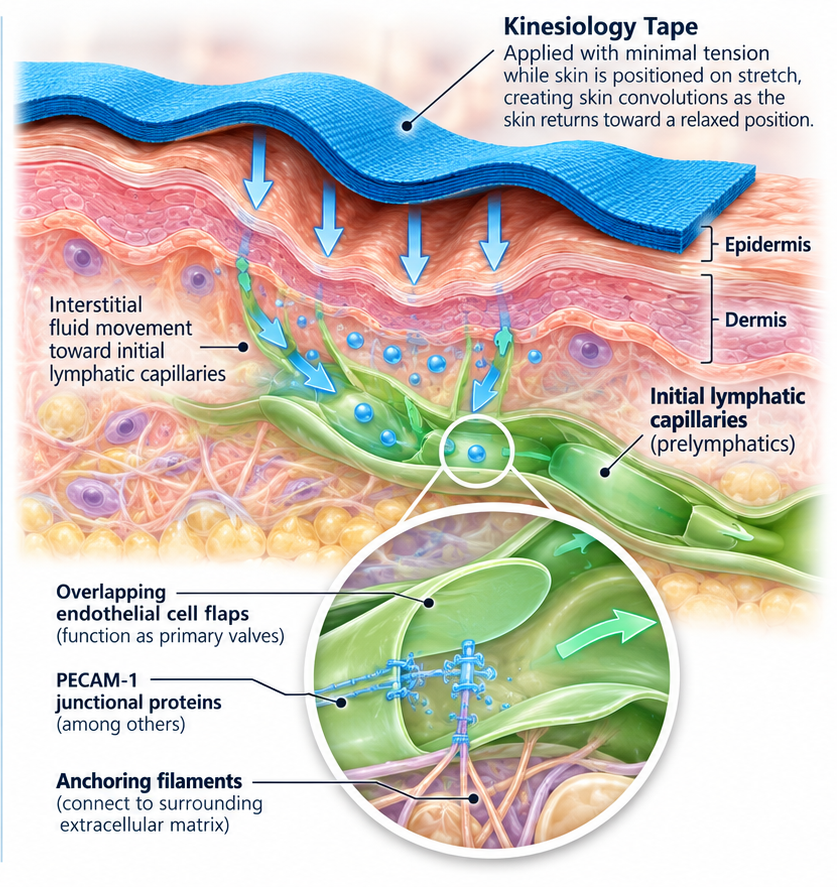
Lymphatic circulation begins with highly permeable, superficial lymph capillaries formed by endothelial cells with junctions between them that allows fluid to pass through with sufficient interstitial pressure. The junctions consist of protein filaments (Platelet Endothelial Call Adhesion Molecule-1 or PECAM-1) originally thought to have a protective or structurally supportive role, however is now believed to play a significant role in how extracellular fluid enters into the lymphatic system. These PECAM-1 filaments appear to be attached to the surrounding tissues and as the surrounding tissue moves, the filaments are pulled and released. This is thought to create a piston-like effect, opening and closing the valves of initial lymphatic capillaries, also known as pre-lymphatics, allowing fluid to enter the system.
Important anatomical distinction: Endothelial junctional proteins, including PECAM-1 (CD31), participate in endothelial biology but should not be equated with the extracellular anchoring filaments themselves. The proposed taping mechanism therefore is described in terms of tissue deformation and initial lymphatic valve mechanics, rather than as a demonstrated direct pumping action of PECAM-1 filaments.
Proposed Biomechanical Model of Lymphatic Augmentation
Traditional descriptions of lymphatic kinesiology taping have frequently emphasized a static lifting effect beneath the tape.
My proposed model places greater emphasis on dynamic mechanical deformation.
When elastic tape is applied to skin that has been comfortably elongated, with minimal or no additional stretch placed on the tape, the skin may develop visible convolutions as the body returns toward a more relaxed position.
These convolutions reflect a mechanical interaction between the elastic tape and the underlying skin.
With subsequent movement, the taped region undergoes repeated changes in tissue tension and deformation.
The central hypothesis is that these changes may influence the mechanical environment surrounding superficial initial lymphatic vessels, potentially assisting their normal fluid-uptake processes.
This concept is consistent with the established importance of mechanical forces in lymphatic physiology. However, the precise effect of kinesiology tape on human initial lymphatic valve function—and the magnitude of any resulting increase in fluid uptake—has not yet been directly established.
Why Application Technique Matters
An important element of this model is the distinction between stretching the tape and positioning the skin on stretch.
Traditional taping instructions have sometimes recommended applying approximately 15–20% tension to the tape.
For the lymphatic application described here, I propose a different strategy: comfortably elongating the skin beneath the intended application area while minimizing tension on the tape itself.
The purpose is to encourage visible convolutions when the skin returns toward a shortened position.
The model proposes that this configuration may increase the dynamic interaction between the tape and the skin during subsequent movement.
Whether this technique is clinically superior to other application methods remains an important question for controlled investigation.
General Application Principles
- Assess the cause of swelling, the condition of the skin, relevant medical precautions, and whether taping is appropriate.
- Position the involved area to comfortably elongate the skin over the intended application site.
- Prepare a fan-shaped or similarly distributed tape configuration when appropriate for the anatomical region.
- Apply the tape with minimal or no additional stretch, maintaining appropriate skin positioning throughout the application.
- Adjust joint or body position as necessary because skin tension changes around different joint axes.
- Allow the body region to return toward a comfortable resting position and observe whether convolutions develop.
- Encourage appropriate, tolerable movement when medically indicated.
These are general educational principles, not a universal treatment prescription. Anatomical location, underlying diagnosis, tissue condition, and patient tolerance should guide clinical decisions.
Clinical Observation: Upper-Extremity Ecchymosis
The photographs accompanying this article document an early clinical application involving bruising of the left upper extremity following an archery-related injury. She had struck her left arm several times when releasing the arrows toward the intended target.
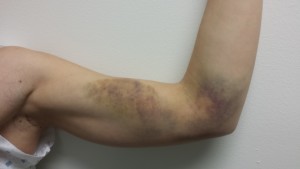
Figure 1: Left arm prior to taping
The tape was applied in narrow strips with the arm positioned to elongate the skin. Minimal tension was placed on the tape itself.
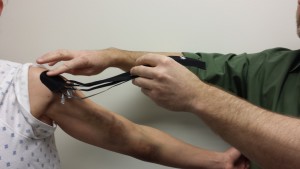

Figure 2: Applying a proximal anchor with absolutely no stretch on the tape and arm positioned with skin on stretch.
Figure 3: Arm positioned so skin is on stretch, no stretch on tape as it is applied
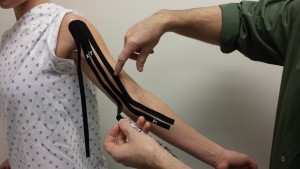
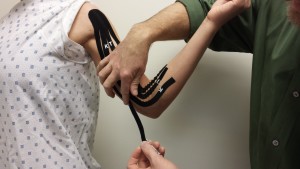
Figure 4: Applying remaining strips with no stretch on tape, continued stretch on skin through positioning
Figure 5: Taking care to place skin on stretch on opposite side of the elbow’s axis of rotation

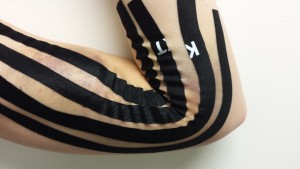
Figure 6: All kinesiology tape from a single application in place
Figure 7: Notice the convolutions where the kinesiology tape lifts the skin.
As the arm returned toward a resting position, visible convolutions developed beneath the strips.
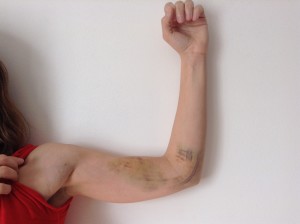
Figure 8: 24 hours after kinesiology tape application. Note the areas where the tape was applied and the marked reduction in ecchymosis/bruising
Photographs obtained approximately 24 hours later demonstrated a visible change in the appearance of the bruised region.
What kinesiology tape enhances is the skin tension and release that occurs with natural active movement of the involved tissues. When applied with the proper technique, kinesiology tape exaggerates the motion of the subcutaneous PECAM-1 filaments, thus augmenting the body’s natural system of removing extracellular fluids and waste.
Figure 10: A closer look at the effect kinesiology tape has when applied using this method. Note the convolutions creating the lymphatic assist where the skin is in a position of “slack” vs. stretch
This clinical observation demonstrates the speed of bruising reduction in the areas of greatest tape convolution. However, an uncontrolled before-and-after observation cannot determine whether the change resulted from taping, natural bruise resolution, variation in lighting or positioning, or other factors. The case is presented as a historical clinical observation and demonstration of application technique—not as controlled evidence of treatment efficacy.
Edema & Lymphedema: Important Differences
Although both involve tissue swelling, edema and lymphedema are not interchangeable diagnoses.
Edema describes abnormal fluid accumulation within tissues and may result from inflammation, trauma, venous dysfunction, systemic disease, or other causes.
Lymphedema results from impaired lymphatic transport capacity. It may occur because of congenital abnormalities, surgery, radiation, malignancy, or other conditions affecting lymphatic drainage.
These conditions can overlap, and chronic swelling often involves interactions between the venous and lymphatic systems.
This distinction matters because a taping strategy considered for localized post-injury swelling cannot automatically be assumed appropriate or effective for chronic lymphedema.
Established lymphedema management may include individualized compression, exercise, skin care, education, and other components of decongestive treatment. Kinesiology taping should be considered, at most, an adjunct where clinically appropriate.
What Does the Research Show?
Research examining kinesiology taping for edema and lymphedema has produced mixed findings.
A particularly interesting experimental study by Shim and colleagues (2003) investigated elastic adhesive tape and lymphatic flow in a rabbit hind-limb model. The authors reported increased lymph flow under certain conditions involving tape and passive movement, suggesting a possible interaction between taping and mechanical activity.
These animal findings provide a rationale for further research but do not establish an equivalent clinical effect in humans.
Human studies have examined kinesiology taping following musculoskeletal injury, orthopedic surgery, and in people with cancer-related lymphedema.
Some trials have reported improvements in swelling-related outcomes, while others have found little benefit or results favoring conventional compression approaches.
The literature also presents methodological challenges:
- Small sample sizes and inconsistent outcome measurements.
- Differences in underlying diagnoses and concurrent interventions.
- Variability in tape configuration, applied tension, and patient positioning.
- Limited direct measurement of lymphatic fluid transport.
- Incomplete reporting of whether tape-induced skin convolutions were achieved.
One of the central arguments of my research commentary is that application technique should be treated as a meaningful experimental variable, rather than assuming all kinesiology taping methods are mechanically equivalent.
At the same time, inadequate reporting of application technique does not, by itself, establish that a negative clinical trial would have been positive with a different method.
Further investigation is needed to determine whether the proposed approach produces clinically meaningful improvements in fluid uptake, edema reduction, or functional outcomes.
Clinical Precautions
Kinesiology tape is generally a low-intensity intervention, but it is not appropriate for every patient or every form of swelling.
Unexplained, sudden, painful, or rapidly worsening swelling requires appropriate medical assessment. Suspected deep vein thrombosis, infection, or systemic causes of edema should not be managed through taping without medical evaluation.
Additional considerations include fragile or injured skin, open wounds, adhesive sensitivity, dermatological conditions, altered sensation, and postoperative precautions.
For individuals with mast cell activation syndrome or other adhesive sensitivities, the possibility of a skin reaction deserves particular attention. Barrier products and adhesive modifications should not be assumed safe or effective without individual assessment.
Tape should be removed if itching, burning, pain, numbness, or other concerning symptoms develop.
Advancing the Research
The proposed biomechanical model suggests several important directions for future investigation.
Research should evaluate whether skin positioning, tape tension, convolution formation, anatomical location, and movement meaningfully influence lymphatic transport.
Ideally, these studies would combine standardized application procedures with objective measures of lymphatic function and clinically relevant outcomes.
Direct imaging of superficial lymphatic transport, where feasible, could help determine whether the proposed mechanical interaction produces measurable physiological changes.
The ultimate goal is not simply to establish whether kinesiology taping can influence swelling, but to understand which mechanisms are involved, under what conditions an effect occurs, and how application methods might be optimized.
Professional Continuing Education
This biomechanical approach has informed my clinical teaching and continuing education work.
I subsequently authored educational material for KT Tape addressing lymphatic anatomy, the proposed mechanism of kinesiology taping, application considerations, and the clinical research.
Clinicians interested in structured professional instruction can explore KT Tape’s official continuing education offerings.
KT Tape Professional Continuing Education Courses
Conclusion
Kinesiology taping for lymphatic uptake augmentation represents an interesting intersection of rehabilitation biomechanics, microvascular physiology, and clinical practice. My proposed model emphasizes the potential importance of dynamic tissue deformation rather than relying solely on a static skin-lifting explanation.
The available literature provides reasons to investigate this approach further, but important questions remain regarding the mechanism, optimal technique, and magnitude of clinical benefit. Careful anatomical interpretation, standardized application procedures, and appropriately controlled studies are necessary to advance our understanding.
Christopher W. Harper, PT, DPT, OCS
EduKT, Inc.
Disclosure: The author has contributed professional educational material to KT Tape and has previously served on the medical advisory board of KT Health, Inc.
Selected References
- Baluk P, et al. Functionally specialized junctions between endothelial cells of lymphatic vessels. Journal of Experimental Medicine. 2007;204(10):2349–2362.
- Schmid-Schönbein GW. Microlymphatics and lymph flow. Physiological Reviews. 1990;70(4):987–1028.
- Shim J, Lee H, Lee D. The use of elastic adhesive tape to promote lymphatic flow in the rabbit hind leg. Yonsei Medical Journal. 2003;44(6):1045–1052.
- Nunes GS, et al. Kinesio Taping does not decrease swelling in acute lateral ankle sprain of athletes: a randomised trial. Journal of Physiotherapy. 2015;61(1):28–33.
- Gatt M, Willis S, Leuschner S. A meta-analysis of the effectiveness and safety of kinesiology taping in the management of cancer-related lymphoedema. European Journal of Cancer Care. 2017;26(5).
- Pekyavaş NÖ, et al. Complex decongestive therapy and taping for patients with post-mastectomy lymphedema: a randomized controlled study. European Journal of Oncology Nursing. 2014;18:585–590.
Applying Kinesiology Tape for Lymphatic Assist:
- Clean the area of application to remove any lotions or skin oils
- Cut tape into strips, creating a “squid” or fork-like design
- Position the area where tape is to applied as to place the skin on stretch
- Place the anchor of the tape strip proximal and medial to the area of treatment
- Apply each cut portion of the tape strip with absolutely no stretch over the area to be treated with the skin remaining on stretch
- Before moving the area out of a position of stretch, gently rub the tape as to create friction for better adhesion
- Proper application will result in convolutions of the tape and skin once the area is returned to a normal position
For this technique to function optimally keep in mind:
Helpful Tips:
- Cut tape into thin strips as to spread a single strip over a larger area
- Place the area to be taped so the skin is on much stretch as possible (within patient comfort and precautions)
- Anchor the tape strip proximally and medially if possible as this follows the pattern of our neurovascular (and lymphatic) structures
- Apply tape with absolutely no stretch on the tape itself over the target area
- Be aware of skin stretch if taping near joints, skin should be on relative stretch as tape is applied, this may require changing position of the joint as you tape
- If tape is applied properly, convolutions in the tape, pulling up gently on the skin should be observed
- Multiple strips can be used in conjunction with each other in a single application, creating lattice designs or “daisy-chaining” multiple strips along the entire extremity
- Movement must take place for KT Tape to enhance the extracellular fluid uptake, often needing nothing more than natural movement that takes place with activities of daily living
- Avoid taping over still healing incisions or wounds as not to avoid disturbing newly developing cells. You can however tape over post-surgical “steri-strips” with caution to avoid the incision itself
- Tape can be worn for 3-5 days, though remove if there are any complaints of itching or other discomfort of any kind
Other Kinesiology Taping for Lymphatic Assist Precautions:
- Consult your physician or therapist before taping with this technique if you have as part of your past medical history
- Cancer
- Active Infection
- Radiation Burns
- Congestive Heart Failure
- Renal Insufficiency
- DVT (Deep Vein Thrombosis)
- Remove tape if you experience:
- Deep ache with tape
- “Tingle” or Numbness
- Skin is “itchy” under or near tape
- Tape “just doesn’t feel good”
Continuing Education & Professional Development
Dr. Harper also authored clinical continuing education material for KT Tape addressing lymphatic anatomy, application considerations, and the scientific rationale underlying these approaches. Healthcare professionals interested in further instruction are encouraged to explore KT Tape’s official clinical continuing education program.
The proposed mechanism remains an area for further scientific investigation. Clinical results may vary, and kinesiology taping should not be considered a replacement for established edema or lymphedema management.